
If your back hurts after a car accident, get a medical evaluation within 72 hours and start documenting everything now. Back pain is a symptom, not a diagnosis, and the specific injury behind it determines your recovery timeline and how strong your insurance claim will be.
Waiting to see if the pain “goes away on its own” is the single most costly mistake we see. Adrenaline from the crash often hides real damage for hours or days, and insurers routinely question claims where treatment started late.
Here is what to do right now:
- Call 911 or go to the ER if you have leg weakness, numbness, or loss of bladder/bowel control.
- Get evaluated the same day or within 72 hours even if pain feels mild or manageable.
- Photograph the scene, your vehicle, and any visible injuries before evidence disappears.
- Start a dated journal logging symptoms, appointments, and how pain affects daily tasks.
- Notify your insurer promptly, per your policy’s reporting window.
Early diagnosis protects two things at once: your spine and your claim. A vague complaint of “back pain” carries far less medical or legal weight than a documented diagnosis tied to the crash date.
Key Takeaways
Early diagnosis and dated documentation, not pain severity alone, determine both your recovery trajectory and the strength of any insurance claim.
| Point | Details |
|---|---|
| Get evaluated within 72 hours | Delayed-onset pain is common; early evaluation ties symptoms clearly to the crash date. |
| Push for a specific diagnosis | “Back pain” alone carries little medical or legal weight compared to a confirmed condition. |
| Know the red flags | Loss of bladder/bowel control, saddle numbness, or progressive leg weakness need emergency care. |
| Pair procedures with rehab | Injections or facet treatments work best combined with active physical therapy, not alone. |
| Document everything from day one | Dated journals, photos, and objective exam findings protect both your health and your claim. |
| Use a referral service like Car Crash Money Atlanta | It connects you to vetted providers and attorneys quickly, at no direct cost for the referral. |
Table of Contents
- Why Back Pain After a Car Accident Happens
- What Symptoms Show Up After a Crash?
- How Doctors Diagnose Crash-Related Back Pain
- What Treatments Actually Work for Crash-Related Back Pain
- How Long Does Back Pain Last After a Car Accident?
- Signs That Mean You Need Emergency Care Now
- Protecting Your Health and Your Claim: Documentation Steps
- What I’ve Learned Watching Crash Victims Navigate This Process
- Get Matched With the Right Providers Fast
- Frequently Asked Questions
- Sources
Why Back Pain After a Car Accident Happens
A collision throws your spine through forces it was never built to absorb in a fraction of a second. Rapid acceleration and deceleration, sudden rotation, seatbelt restraint forces, and axial loading (the compressive force of your body slamming down through the spine) each damage different structures. That’s why two people in the same crash can walk away with completely different injuries.
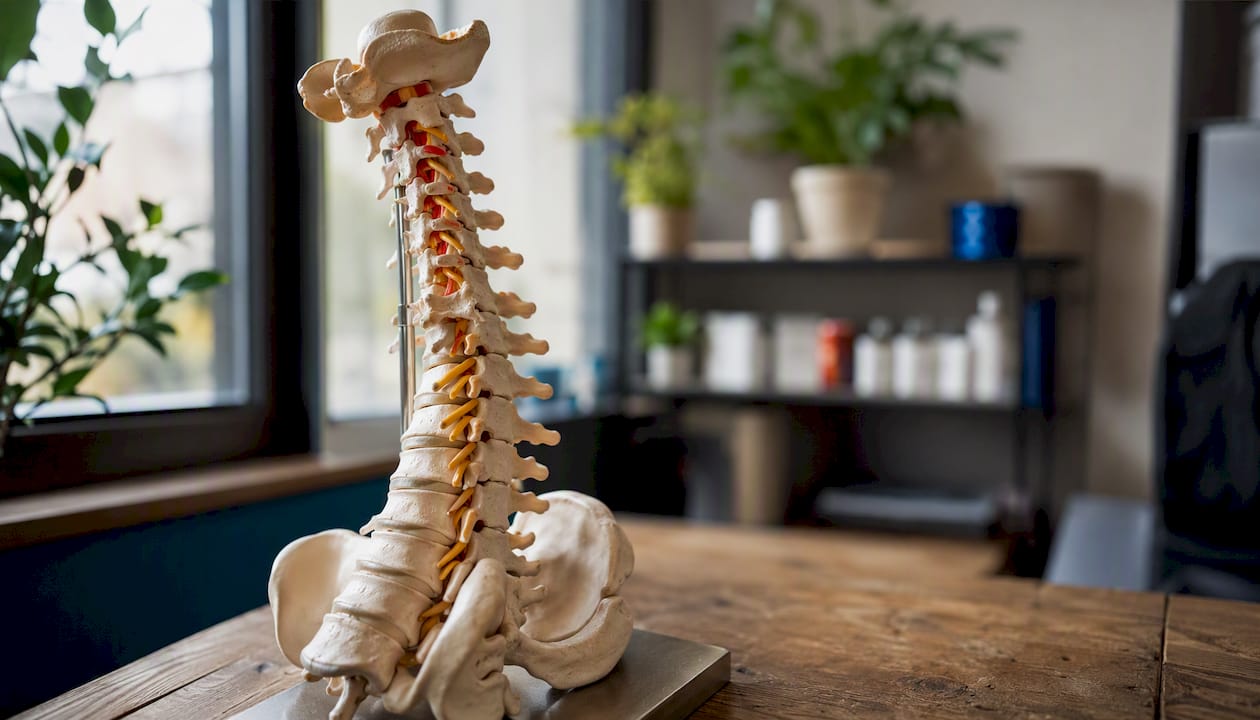
Understanding the mechanism helps explain why “lower back pain car accident” cases vary so widely in severity and treatment. A rear-end collision tends to whip the torso forward while the pelvis stays anchored by the seatbelt, straining muscles and ligaments. A side-impact crash often twists the spine, stressing the facet joints. High-speed frontal impacts can compress vertebrae outright.
Common diagnoses following a crash include:
- Lumbar sprain or strain — stretched or torn muscles and ligaments, usually worse with movement and better with rest.
- Facet joint irritation — localized pain that worsens with extension or twisting, often mistaken for a simple muscle strain.
- Herniated or bulging disc — disc material pressing on a nerve root, frequently causing radiculopathy (pain, numbness, or weakness radiating down a leg).
- Sacroiliac joint injury — pain at the base of the spine near the pelvis, often triggered by twisting or standing from a seated position.
- Compression fracture — a cracked or collapsed vertebra, more common in high-energy crashes or in people with lower bone density.
- Sciatica — not a diagnosis itself, but a symptom describing nerve pain radiating along the sciatic nerve, usually from disc or facet involvement.
The crash mechanics behind whiplash injuries also apply to the lower back. The same forces that strain neck tissue can injure lumbar structures simultaneously, which is why a full spine evaluation matters even when neck pain feels like the main complaint.
Pro Tip: Pay attention to how the pain behaves, not just where it hurts. Pain that radiates below the knee usually points toward disc-related nerve irritation. Pain that stays above the knee and worsens with backward bending often signals a facet joint problem. Tell your doctor exactly how the pain moves and changes, since that detail often distinguishes disc-related pain from facet pain and shapes the entire treatment plan.
A precise diagnosis, not the generic label “back pain,” changes both your treatment path and your claim’s legal value. Insurance adjusters and defense attorneys look for a documented, specific condition tied clearly to the crash. “Back pain” alone invites skepticism. “L4-L5 disc herniation with radiculopathy confirmed on MRI” does not.
What Symptoms Show Up After a Crash?
Immediately after a collision, expect tenderness, stiffness, muscle spasm, and localized soreness around the injured area. These symptoms often feel manageable at first, which is part of the problem.

Many people feel fine at the scene and then wake up the next morning barely able to move. Delayed-onset pain 24 to 72 hours after a crash is common because adrenaline masks pain signals in the immediate aftermath, and inflammation builds gradually as damaged tissue swells and stiffens.
Watch for these developing symptoms in the days after your accident:
- Increasing stiffness or reduced range of motion
- Pain that starts radiating into a hip, thigh, or leg
- Numbness, tingling, or a “pins and needles” sensation
- Muscle weakness in one or both legs
- Pain that worsens with sitting, standing, or specific movements
Radiating pain paired with numbness or weakness usually points toward nerve involvement (radiculopathy) rather than simple muscle strain. This distinction matters clinically because nerve-related injuries often need imaging and a different treatment approach than a soft-tissue sprain.
A small number of symptoms cross the line from “concerning” to “emergency.” Loss of bladder or bowel control, numbness in the groin or inner thighs (saddle numbness), or progressive leg weakness require immediate care, covered in detail further below.
How Doctors Diagnose Crash-Related Back Pain
Your evaluation should start with a focused history: when the pain started, how the crash happened, whether pain radiates anywhere, whether you’ve noticed bowel or bladder changes, and whether you had spine issues before the accident. This history shapes everything that follows.
Physical exam maneuvers tell your clinician a lot before any imaging happens. A straight leg raise test that reproduces radiating leg pain suggests nerve root irritation. Focal, pinpoint midline tenderness raises suspicion for a fracture. Limited range of motion in specific directions, like pain that worsens with backward bending, points toward facet joint involvement.
Imaging isn’t automatic, and that’s by design. Guidelines recommend a focused history and exam first, with imaging ordered based on red flags or focal neurologic deficits rather than routinely on day one. Here’s how the three main options typically get used:
- X-ray — ordered when fracture is suspected, especially after high-energy impact or with focal bony tenderness.
- CT scan — preferred when detailed bone imaging is needed, such as confirming or characterizing a suspected fracture.
- MRI — ordered when a disc injury or nerve involvement is suspected, or when neurologic symptoms persist beyond the initial visit.
This exam-led, imaging-second approach isn’t a cost-cutting shortcut. A structured clinical pathway that screens for red flags before ordering tests reduces unnecessary imaging while still catching true neurologic compromise.
For your claim, documentation from this process matters as much as the treatment itself. Contemporaneous notes, objective exam findings (not just “patient reports pain”), and imaging that ties the injury to the crash date all strengthen your case later.
Pro Tip: If the ER discharged you with pain medication and a “follow up as needed” note, don’t let it slide. Book a follow-up with a spine specialist or your primary care doctor within the same week. Early follow-up creates the documentation trail that both your recovery and your claim depend on.
What Treatments Actually Work for Crash-Related Back Pain
Treatment almost always starts conservative and escalates only if your symptoms and imaging justify it. Jumping straight to injections or surgery without trying active care first is rarely the right call, and it’s rarely what evidence-based guidelines recommend.
The typical sequence looks like this:
- Protect neurologic safety — rule out fracture, cauda equina, or progressive nerve damage before anything else.
- Control pain enough to move — short-term non-opioid medication, ice or heat, and activity modification to keep you functional without overprotecting the injury.
- Rebuild function — physical therapy, graded exercise, and posture or ergonomic adjustments to restore strength and range of motion.
- Escalate only if warranted — injections or surgical consultation when the pattern of symptoms and imaging findings support it.
NIAMS confirms that most acute low back pain improves with conservative care and active rehabilitation rather than immediate surgery or prolonged bed rest. Passive rest sounds appealing when you’re in pain, but prolonged inactivity actually slows recovery and weakens supporting muscles further.
When conservative care stalls, targeted procedures like epidural steroid injections or facet joint injections may reduce inflammation enough to let physical therapy work more effectively. These aren’t standalone fixes. They’re paired with active rehab, not substitutes for it.
Surgery enters the conversation in specific scenarios: a progressive neurologic deficit, persistent radicular pain matched to a confirmed disc herniation on imaging, or an unstable fracture. These cases are the exception, not the rule.
On medication safety, NSAIDs help with inflammation short term, but talk with your treating clinician about duration and dosage. Opioids carry real dependency risk and should be coordinated carefully, used briefly, and paired with a plan to taper off.
Pro Tip: Passive treatment alone, like injections without follow-up exercise, tends to produce short-lived relief. Pairing procedures or manual therapy with active rehabilitation produces better long-term outcomes than either approach used in isolation.
How Long Does Back Pain Last After a Car Accident?
Recovery timelines vary by diagnosis, but most soft-tissue injuries, sprains and strains, improve steadily over several weeks with consistent rehab. Disc-related radiculopathy often takes longer, sometimes weeks to a few months, and the exact path depends on severity and how early treatment started.
Several factors make chronic back pain more likely:
- Higher pain intensity in the first days after the crash
- Multiple overlapping symptoms (radiating pain plus numbness plus weakness)
- Delayed medical care after the accident
- Preexisting spine conditions or prior back injuries
- Psychological distress, anxiety, or depression following the trauma
Delayed evaluation doesn’t just complicate a claim. It genuinely harms recovery odds, since untreated inflammation and guarding patterns tend to compound over time.
Expect steady, if gradual, improvement week over week. If your pain plateaus or worsens instead of trending better, that’s a signal to go back to your provider and reassess the diagnosis rather than simply continuing the same treatment plan.
Signs That Mean You Need Emergency Care Now
A short list of symptoms means stop reading and get to an emergency room immediately. These aren’t “wait and see” situations.
- Loss of bladder or bowel control
- Saddle numbness (numbness in the groin, inner thighs, or buttocks)
- Sudden, progressive leg weakness or foot drop
- Severe midline spinal tenderness following high-energy trauma
- Chest pain, abdominal pain, or difficulty breathing alongside back pain
Progressive leg weakness, saddle numbness, and loss of bladder or bowel control together point to cauda equina syndrome, a surgical emergency requiring urgent imaging and decompression. Waiting even a day can mean permanent nerve damage.
If you’re unsure whether a symptom counts as an emergency, treat the uncertainty itself as the answer. Go get evaluated. No back pain claim or scheduling conflict is worth risking permanent neurologic damage.
Protecting Your Health and Your Claim: Documentation Steps
Strong medical documentation and a strong legal claim are built from the same evidence. Do these steps in roughly this order:
- Get medical care immediately and make sure every visit generates a written record.
- File a police report if one wasn’t completed at the scene, especially for any collision involving injury.
- Photograph the scene, vehicle damage, and visible injuries before anything gets repaired or heals.
- Keep a dated symptom and treatment journal, noting pain levels, missed work, and functional limits.
- Notify your insurer within your policy’s required reporting window.
Your medical records need specifics, not vague complaints. Push your provider to document exact dates, objective exam findings (like a positive straight leg raise or measured range-of-motion loss), functional limitations, referrals, and imaging results. A record that says “L5 radiculopathy confirmed on MRI, positive straight leg raise, unable to lift over 10 pounds” is dramatically more persuasive than “patient reports back pain” when an adjuster or attorney reviews your file.
Consider talking to a personal injury attorney if you’re facing persistent disability, mounting medical bills, permanent impairment, or an insurer that’s slow-walking your claim. Early legal consultation isn’t just about the eventual settlement. It helps coordinate your medical documentation from the start, which strengthens the case as it develops. Georgia residents dealing with these questions can review the Georgia car accident injury claim process for state-specific guidance on timing and next steps.
Pro Tip: Keep every document in one place, a folder, an app, whatever works, including clinic intake forms, discharge instructions, photos, and copies of every bill. Scattered documentation is the number one reason strong medical cases turn into weak insurance claims.
What I’ve Learned Watching Crash Victims Navigate This Process
The gap between how people think claims work and how they actually work is enormous. Most victims assume the pain itself is the evidence. It isn’t. The evidence is the paper trail: dated records, specific diagnoses, objective findings, and a clear timeline connecting the crash to the treatment.
A referral service changes that equation in a concrete way. When someone gets matched quickly with a spine specialist instead of waiting weeks for a primary care referral, two things happen simultaneously: their treatment starts sooner, and their documentation starts sooner. Those aren’t separate benefits. They’re the same benefit viewed from two angles.
What stands out about a coordinated referral approach is how it removes the guesswork victims otherwise face alone: which provider treats crash injuries specifically, which attorney handles cases like theirs, and how to keep medical and legal threads connected instead of tangled. Car Crash Money Atlanta connects victims to vetted personal injury attorneys and medical professionals without charging the victim directly for that referral. The value isn’t the introduction itself. It’s the coordination that follows, where medical documentation and legal strategy move together instead of at cross purposes.
Get Matched With the Right Providers Fast
Car Crash Money Atlanta exists for exactly the moment you’re in right now: back pain, a lot of questions, and no clear starting point. Instead of spending days researching spine specialists or vetting personal injury attorneys on your own, one call connects you to both, matched to your specific situation.
There’s no cost to you for the referral itself. Car Crash Money Atlanta works with attorneys and medical providers directly, which means you get fast access to trusted professionals without adding another bill to the pile. Timing matters here too. The sooner your treatment and documentation start, the stronger your position if a claim becomes necessary later, and our referral network is built to move fast on both fronts at once.
Save our number or bookmark the Car Crash Money Atlanta homepage now, before pain or scheduling stress makes it harder to act. If your injuries are severe or an insurer is already pushing back, look into policy limit strategies built specifically for cases like yours.
Frequently Asked Questions
How soon should I see a doctor for back pain after a car accident?
Get evaluated the same day or within 72 hours, even if the pain feels mild. Delayed-onset symptoms are common as inflammation develops, and early records strengthen any future claim.
Can back pain from a car accident show up days later?
Yes. Adrenaline often masks pain at the scene, and inflammation frequently causes symptoms to appear or worsen 24 to 72 hours after the crash.
What’s the difference between disc pain and facet joint pain?
Disc-related pain often radiates below the knee and may include numbness or weakness. Facet joint pain typically stays above the knee and worsens with backward bending or twisting.
Do I need an MRI right after a car accident?
Not necessarily. MRI is usually reserved for suspected disc or nerve involvement or persistent neurologic symptoms, while X-ray covers suspected fractures and CT provides detailed bone imaging.
How does pain and suffering get calculated in a back injury claim?
Insurers and attorneys typically apply a pain and suffering multiplier to your medical expenses and lost wages, with the multiplier increasing alongside injury severity, treatment duration, and documented impact on daily life.
Why does documentation matter so much for a claim?
A specific, well-documented diagnosis with objective exam findings and imaging is far more persuasive to an insurer than a vague complaint of general back pain, and it directly affects settlement value.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- PMC
- Mayo Clinic — When to see a doctor about back pain
- NIAMS
- Johns Hopkins Medicine — Whiplash injury